


Thyroid embolization is a non-surgical method performed by entering through the blood vessels without making any incision in the neck and cutting off the blood flow only to the diseased nodule to enable it to shrink, whereas thyroid surgery is the surgical removal of the tissue or the entire organ from the body under general anesthesia. This fundamental distinction directly shapes patients’ lives after treatment. Since the patient’s own thyroid gland is preserved in the embolization method, the possibility of permanent dependence on hormone medication after the procedure is largely eliminated. In surgery, however, external synthetic supplementation is generally required because of organ loss. These two approaches, which differ completely from each other in terms of the type of anesthesia applied, length of hospital stay, and aesthetic integrity, offer entirely different recovery processes centered on preserving the patient’s own organ.
What Are the Conventional Treatments for Thyroid Diseases and Why Has Thyroid Embolization Come to the Fore?
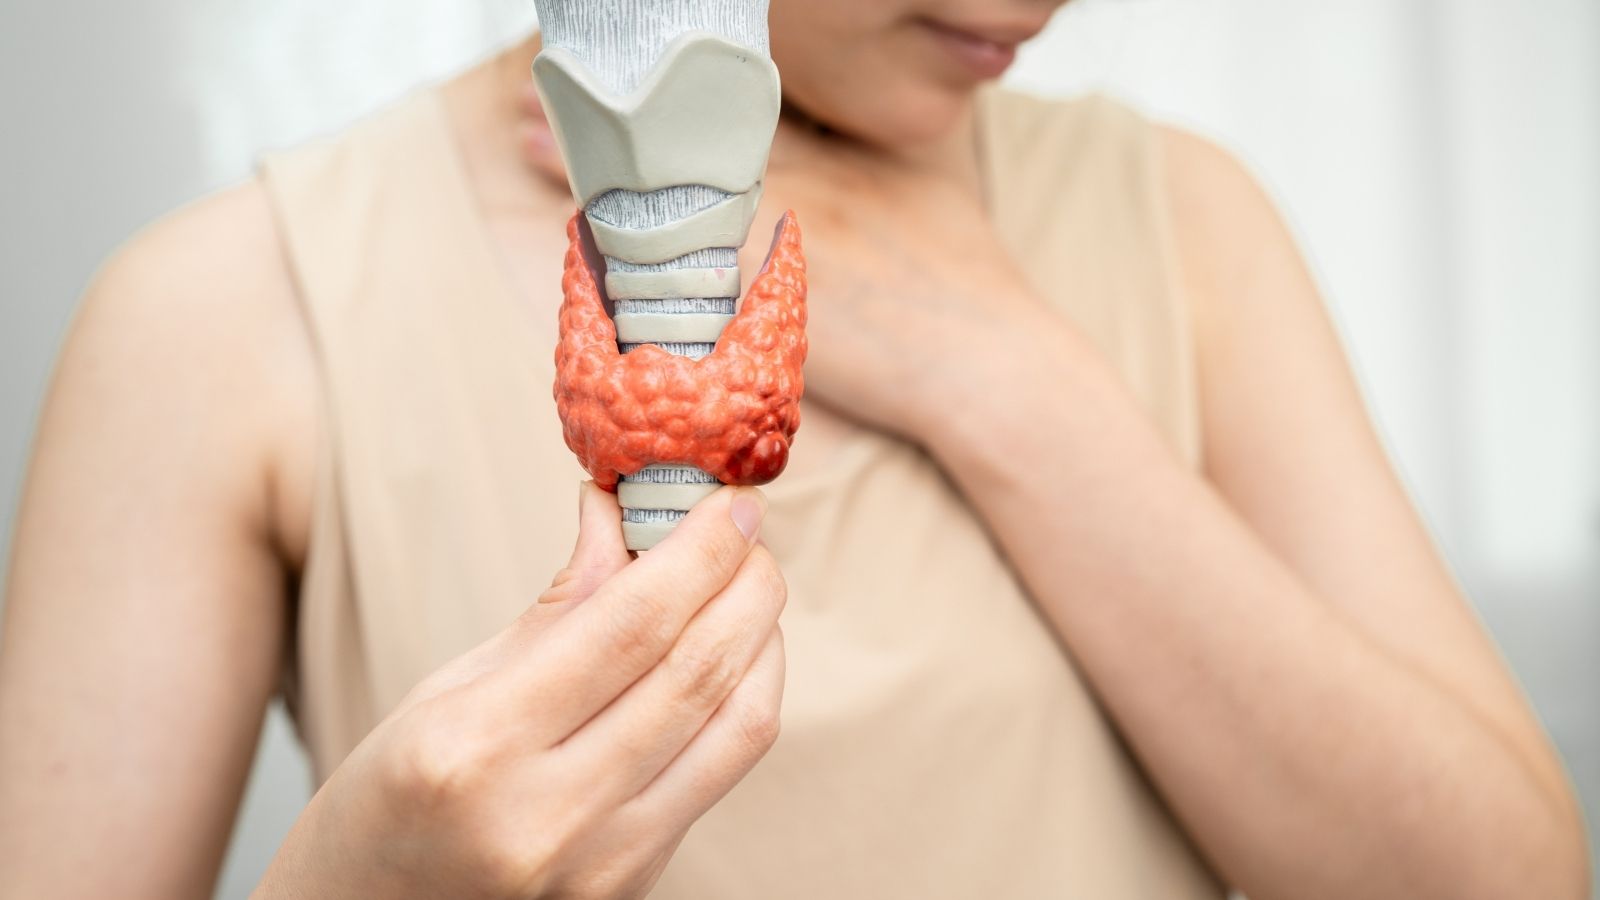
The thyroid gland, located in the front part of the neck just above the windpipe and resembling a butterfly in shape, is a vital organ that regulates the body’s energy metabolism, heart rhythm, body temperature, and overall operating pace. In cases where this important organ becomes diseased or masses called nodules grow within it, the medical world has generally relied on three main treatment methods for many years. These are medication treatments, radioactive iodine applications, and surgical operations.
Although medication treatments are generally the first option attempted when the thyroid is overactive, long-term use of these medications may sometimes strain liver functions or lead to various systemic side effects. Radioactive iodine treatment, which comes into play when medications are insufficient or cause side effects, is a method that cannot be applied comfortably to every patient because it contains radiation and may increase complaints, especially in patients with eye involvement.
Traditional surgery, regarded as the final and most definitive solution, meaning the surgical removal of the thyroid gland from the body, has been a frequently used standard for decades. However, the permanent effects this method leaves on patients are quite serious. Complete removal of the thyroid gland generally makes the patient dependent on taking external synthetic hormone tablets for life. In addition, because of the complex anatomy of the neck region, there is a possibility of encountering undesirable conditions inherent to the nature of surgery, such as damage to the nerves controlling the vocal cords or injury to the parathyroid glands that regulate calcium balance. In order to avoid the fatigue of general anesthesia, prevent a suture scar on the neck, and reduce lifelong medication use by preserving the organ, technological advances in medicine have led to new searches. At this point, closed and non-surgical treatment methods such as thyroid embolization, which intervene only in the patient’s diseased tissue, have taken their place in medical practice as a modern alternative.
What Effect Does Thyroid Embolization Create in the Body and How Does It Differ from the Logic of Thyroid Surgery?
In the clearest terms, thyroid embolization is the process of blocking from within, using angiographic methods, the blood vessels of nodules that grow inside the thyroid gland and harm the patient. Every living tissue and every growing mass in the human body needs fresh blood, oxygen, and nutrients coming from the arteries in order to survive. If the nourishment of a tissue through the blood is prevented, that tissue cannot maintain its vitality and begins to shrink. The basic biological logic of the embolization procedure is based on this rule.
In this method, no scalpel incision is made in the neck region. By advancing through the blood vessels, the very fine capillary vessels directly supplying the diseased nodule are identified. Thanks to special occlusive substances injected into these fine vessels, only the blood flow of the mass is selectively slowed or stopped. The nodular tissue whose blood flow has been cut off enters a stage of losing its vitality over time due to oxygen deprivation. This tissue, which can no longer receive nourishment, contracts and decreases in volume.
Perhaps the most favorable aspect of this process is that the body’s own natural cleansing systems come into play. The immune cells in our body slowly and safely phagocytose these cells that have lost their vitality, meaning they engulf them and remove them from the area. In this way, the patient has the opportunity to be relieved of the problematic nodules without the neck being cut and while largely preserving healthy thyroid tissue. In the surgical method, however, the mass is physically cut out and removed together with some surrounding healthy tissue or the entire thyroid gland. While embolization works on the principle of drying the tissue from within, surgery works on the principle of physically cutting and removing it.
How Is Thyroid Embolization Performed and Does It Require General Anesthesia Like Thyroid Surgery?
This innovative treatment approach is performed not in the conventional and cold operating room environments we are familiar with, but in angiography units equipped with high-technology imaging systems. One of the issues that provides patients with the greatest relief is the form of anesthesia. General anesthesia, meaning completely putting the patient to sleep and connecting them to a ventilator, is generally not required for the procedure. To ensure the patient’s comfort and relieve anxiety, only relaxing medications are administered intravenously, and the entry area is numbed with local anesthesia. The patient remains awake during the procedure, breathes comfortably, and can communicate with the physician.
The procedure is generally started by entering through the artery in the groin region or, in recent years, through the vessel in the wrist, which is a much more comfortable option for patients. Very thin, flexible tubes approximately the thickness of spaghetti are placed inside the vessel through only a small needle hole. Thanks to real-time screen images provided by advanced X-ray devices, the physician advances these tubes painlessly along with the blood flow and reaches the main vessels supplying the thyroid in the neck region. Since there are no pain nerves on the inner surface of the vessels, the patient does not feel the tube advancing inside the body.
Once the target area is reached, much thinner microtubes, almost the thickness of a strand of hair, are sent through the main tube. In this way, the pathways supplying healthy tissues are bypassed and the terminal branches directly supplying the nodule are entered. At this stage, occlusive agents come into play. When special particles resembling microscopic grains of sand are released into the vessel, they fill the capillary vascular network of the nodule like a plug. The physician determines the appropriate particle size according to the patient’s anatomy and the structure of the nodule and takes great care to ensure that the procedure remains limited to the targeted vascular network. When the flow to the mass stops, the procedure is completed, and the patient is taken to the room shortly afterward to rest.
How Are the Vocal Cords Protected During Thyroid Embolization and What Are the Risks of Thyroid Surgery?
The side effects of traditional thyroid surgery that cause the greatest concern for patients are the possibility of damage to neighboring organs because of the narrow anatomy of the neck region. The neck region is almost like a busy highway junction; the windpipe, esophagus, carotid arteries, and highly important nerves run very close to one another. Hoarseness resulting from injury to the nerves that move the vocal cords or damage to the calcium glands (parathyroid glands) located immediately behind the thyroid are among the general risks involved in surgery. Thyroid embolization, however, reduces these risks to very low levels thanks to its anatomical approach.
During the embolization procedure, there is no cutting, separating, or pulling of tissues from the outside inward. Everything proceeds through the vessel within a closed channel system. The vascular supply connections of the nerves moving the vocal cords are different from the embolization target. Therefore, a situation such as accidentally cutting or damaging these nerves mechanically, as may occur in surgery, generally does not arise. Nerve integrity largely remains in its natural state.
Preserving the parathyroid glands requires special attention from the physician. The parathyroid glands regulate calcium balance and are adjacent to the fine vessels supplying the thyroid. During the closed procedure, physicians carefully examine the fine vascular separations on high-resolution screens and direct the occlusive particles beyond the branches supplying the parathyroid, only into the nodule. In addition, to prevent permanent calcium deficiency, all of the main vessels supplying the thyroid are not closed at the same time; the aim is to allow the parathyroid glands to continue receiving blood from healthy tissue.
Which Patients Are Suitable for Thyroid Embolization and Who Should Undergo Thyroid Surgery?
Thyroid embolization is a strong alternative for patients who do not want surgery or for whom receiving anesthesia is risky. Since each patient’s anatomy and the course of the disease are different, treatment selection should be individualized. There are main patient groups in whom this method is frequently applied.
Some conditions considered suitable for the procedure include:
- Patients with toxic goiter
- Those with large, compressive nodules
- Cases of goiter extending into the chest cavity
- Individuals carrying surgical risk
This method may be an effective balancing option in cases of thyroid overactivity, also known as toxic goiter, that cannot be controlled with medications. Large nodules that have grown enough to be externally visible in the neck region, cause aesthetic discomfort, create shortness of breath by pressing on the windpipe, or cause difficulty swallowing are among the areas where embolization is frequently applied. In goiters that grow downward into the chest cavity and require major operations such as opening the breastbone for surgical removal, intervening from within through the blood vessels provides significant comfort. In addition, patients for whom general anesthesia is risky because of advanced age or heart or lung diseases have an opportunity for treatment with this method. In the definitive treatment of malignant diseases such as thyroid cancer, however, the general approach is to completely remove the tumorous tissue from the body surgically; therefore, patients with a confirmed cancer diagnosis are generally directed to thyroid surgery.
What Are the Main Differences Between Thyroid Embolization and Thyroid Surgery?
At the current point reached by modern medicine, there are practical and clear distinctions that patients should know regarding their treatment processes. There are significant differences in patient experience between surgically cutting out diseased tissue and drying it from within through angiographic methods.
The main categories of differences between the two methods are as follows:
- Type of anesthesia
- Incision scar on the neck
- Length of hospital stay
- Need for permanent hormone medication
- Risk of hoarseness
The most obvious difference is the anesthesia applied. Operations are mostly performed under general anesthesia, in which the patient is completely put to sleep, whereas closed procedures are performed while the patient is awake using local anesthesia that numbs only the area. From an aesthetic perspective, surgical intervention leaves a permanent suture scar on the front of the neck, whereas procedures entered through the vessel leave no scar on the neck. The recovery speed is also quite different; after surgery, patients generally remain in the hospital for several days with drainage tubes removing accumulated fluid from their necks, while patients undergoing embolization are usually discharged on the same day and return to their daily lives. One of the most vital differences concerns the condition of the organ; since the thyroid gland is removed in surgery, lifelong synthetic hormone tablet use is generally required, whereas the possibility of medication dependence is greatly reduced in the other method because healthy tissue remains in place.
How Are Thermal Ablation Methods Combined with Thyroid Embolization and Are They Used Before Thyroid Surgery?
Another advanced approach offered by interventional procedures is needle ablation methods performed by viewing the area from outside through the skin using ultrasound. If the structure of the nodule is solid like a piece of flesh, thermal ablation technologies called radiofrequency or microwave are used. In these procedures, the center of the nodule is entered with a thin needle under local anesthesia, and the diseased tissue is dried from within using controlled heat energy emitted from the needle tip.
An important detail that increases the safety of these procedures is the creation of a cold water cushion by injecting a special fluid between the thyroid capsule and surrounding critical organs before the procedure. Thanks to this liquid shield, the heat is largely prevented from reaching the vocal cords or other tissues.
In some cases, the nodule is so large or has such extensive blood flow that the heat delivered only by the needle may not be sufficiently effective because of the rapid blood circulation. In such very large masses, these two different non-surgical methods are combined. First, the arterial blood supply of the nodule is cut off through angiography. Then, heat treatment is applied with a needle to this mass whose blood flow has been stopped. With this combined approach, the aim is to achieve very significant shrinkage even in enormous masses that are extremely difficult to operate on. In addition, if surgical removal of a giant mass is planned, embolization may be performed as preparation a few days before surgery in order to prevent dangerous bleeding that may occur during the operation and make the surgeon’s work easier.
What Is the Recovery Process After Thyroid Embolization and How Long Does It Take Compared with Recovery After Thyroid Surgery?
While the mass is removed from the body all at once during the operation in surgical procedures, the shrinking and disappearance of the treated tissue in non-surgical methods is a biological process that takes place over time. The body’s cleansing cells naturally eliminate this tissue that has lost its vitality over the course of months. The results do not appear the moment the procedure ends but gradually emerge over weeks and months.
The follow-up intervals during the recovery process are as follows:
- The first week
- The first month
- The third month
- The sixth month
- The first year
During the first days following the procedure, very mild edema in the neck region and tenderness when touched externally may be felt. Since the tissue begins to break down, a certain amount of thyroid hormone stored inside the nodule may enter the bloodstream and create short-term fluctuations in test results, but this condition generally balances itself. By the first month, hormone values have usually returned to normal, and ultrasound examinations reveal that the mass has begun to deflate from within.
By the third month, the biological cleansing process accelerates; externally, the swelling in the neck is observed to begin subsiding. More importantly, because the physical pressure exerted by the mass on the windpipe and esophagus is reduced, the patient begins to experience major relief in complaints such as difficulty breathing and swallowing. By the sixth month, a very significant reduction in nodule volume is targeted, and most clinical symptoms have disappeared. At the end of the first year, the mass that made the patient’s life difficult before the procedure has largely lost its volume and transformed into an inactive, silent scar that can barely be detected even with imaging devices. This indicates that recovery has largely been completed.
What Are the Side Effects of Thyroid Embolization and How Different Are They from the Risks of Thyroid Surgery?
No intervention performed in medicine is completely risk-free, but the main starting point of non-surgical methods is to reduce the severe or permanent risks carried by traditional surgery as much as possible. The safety profile of these procedures is generally quite favorable for patients. Nevertheless, as with every medical intervention, there are certain natural reactions and temporary side effects produced by the body. These side effects are part of the body’s physiological response to the treatment and changes in the tissue.
Some effects that may occur after the procedure include:
- Sore throat
- Tenderness while swallowing
- Mild fever
- Temporary muffled voice
- Jaw or tooth pain
- Swelling in the neck region
The most frequently encountered conditions are generally mild sore throat and a stinging sensation while swallowing. This condition closely resembles the throat sensitivity experienced during an ordinary upper respiratory tract infection. In addition, the body may develop a mild fever in response to the tissues being broken down. Edema occurring in the neck region after the procedure may place slight pressure on the nerves and create temporary muffling of the voice, but since there is generally no permanent nerve transection as in surgery, this condition usually improves within a short time. Mild referred pain radiating to the area beneath the jaw and to the teeth may sometimes occur. Almost all of these symptoms are temporary conditions that can easily be brought under control within a few days using standard pain relievers and anti-edema medications recommended by your physician in the hospital or at home. Although very rare vascular problems may occur, the probability of these major risks developing is extremely low with modern devices and in experienced hands.
Why Should the Thyroid Embolization Option Be Evaluated Before Deciding on Thyroid Surgery?
Advances in medical science have shifted the understanding of treatment from the logic of “completely sacrificing the diseased organ” toward the philosophy of “solving only the problem while preserving the healthy parts of the organ.” Thyroid embolization and similar closed methods offer a highly contemporary perspective in the treatment of thyroid diseases through their aesthetic results that leave no suture scar on the neck, their structure that allows the patient to continue producing natural hormones, their comfort that does not require long hospital stays, and their technique that reduces surgical risks such as hoarseness.
The existence of such organ-preserving methods is a major opportunity, especially for patients with chronic diseases, those of advanced age, or those who must face a difficult surgical process because of a mass in the neck that has reached a serious size. Before undergoing thyroid surgery and giving up the entire organ or becoming obliged to take tablets every day for life, investigating whether your condition is suitable for non-surgical methods is a highly appropriate step for your quality of health. Before making a decision, obtaining opinions from specialists in different fields who are experienced in thyroid diseases, particularly consulting physicians experienced in closed endovascular treatments, is the most valuable investment you can make in your own body and future quality of life. Determining which path is more suitable for your life while dealing with your disease is the most fundamental factor that will increase treatment success.
Frequently Asked Questions
What are the main differences between thyroid embolization and thyroid surgery?
In thyroid embolization, the aim is to shrink the nodule by closing the vessels supplying it, whereas in thyroid surgery, the nodule or part or all of the thyroid gland is surgically removed. Treatment selection is determined according to the patient’s clinical condition.
For which patients may thyroid embolization be an alternative to thyroid surgery?
Thyroid embolization may be considered an alternative option in suitable patients with benign, symptomatic thyroid nodules who have a high surgical risk or do not want surgery. Suitability is determined through detailed examination.
Is there a difference between the recovery time of thyroid embolization and thyroid surgery?
Thyroid embolization may generally provide a shorter hospital stay and a faster return to daily life. In thyroid surgery, recovery time may vary according to the extent of the surgery and the patient’s general health condition.
Can the thyroid gland be completely preserved after thyroid embolization?
Since thyroid embolization aims to reduce the blood supply of the targeted nodule, most of the thyroid tissue may be preserved. However, results may vary according to the structure and size of the nodule and the technique applied.
Is thyroid surgery or thyroid embolization more effective?
The effectiveness of both methods varies according to the disease being treated. Surgery takes priority in cases with suspected cancer, whereas embolization may provide successful results in selected benign nodules.
What are the possible risks of thyroid embolization and thyroid surgery?
Pain, temporary fever, or vascular-related complications may occur with embolization. In surgery, risks such as bleeding, infection, vocal cord nerve injury, and effects on the parathyroid glands are evaluated.
Do nodules disappear completely after thyroid embolization?
After thyroid embolization, nodules generally shrink over time, and complaints related to compression may decrease. However, complete disappearance of the nodule is not expected in every patient, and regular follow-up is important.
Which examinations should be performed before thyroid embolization and thyroid surgery?
Thyroid ultrasonography, blood tests, fine-needle aspiration biopsy when necessary, and other imaging methods may be performed. These evaluations help determine the most appropriate treatment option.
Is thyroid hormone use required after thyroid embolization?
Thyroid functions may be preserved in most patients, but this is not the same for every patient. Hormone levels are monitored after treatment, and thyroid hormone therapy may be initiated only when considered necessary.
How is the choice made between thyroid embolization and thyroid surgery?
The treatment decision is made by a specialist team by jointly evaluating whether the nodule is benign or malignant, its size, the complaints it causes, thyroid functions, the patient’s general health condition, and expectations.





Vaka Örnekleri